
Sorting out gluten sensitivity vs. celiac disease — and wheat allergy, the third condition people often leave out of the conversation — matters more than it first appears. The three have different causes, different tests, and very different treatments, and the one you have decides how strict you need to be for the rest of your life.
Maybe this sounds familiar. You have had bloating, cramping, and diarrhea, along with stretches of fatigue and brain fog that are hard to explain. You have tracked it, read about it, and talked with other people, and everything seems to point at gluten. So is gluten a real problem for you, or just a buzzword? The honest answer is that your symptoms alone cannot tell you. But the right tests can, and the order you do them in matters enormously.
Jump to frequently asked questions →
What is the quick difference between the three?
| Wheat allergy | Gluten sensitivity | Celiac disease | |
|---|---|---|---|
| What it is | Allergic reaction to wheat proteins | Symptoms after gluten, trigger unclear | Autoimmune disease |
| Triggered by | Wheat only | Wheat, rye, barley | Wheat, rye, barley |
| Damages intestine | No | No | Yes |
| Symptoms start | Minutes to 2 hours | Hours to days | Hours to days, or never |
| Confirmed by | Allergist testing | Ruling out the other two | Blood test, then biopsy |
| Treatment | Avoid wheat | Limit or avoid gluten | Strict gluten-free for life |
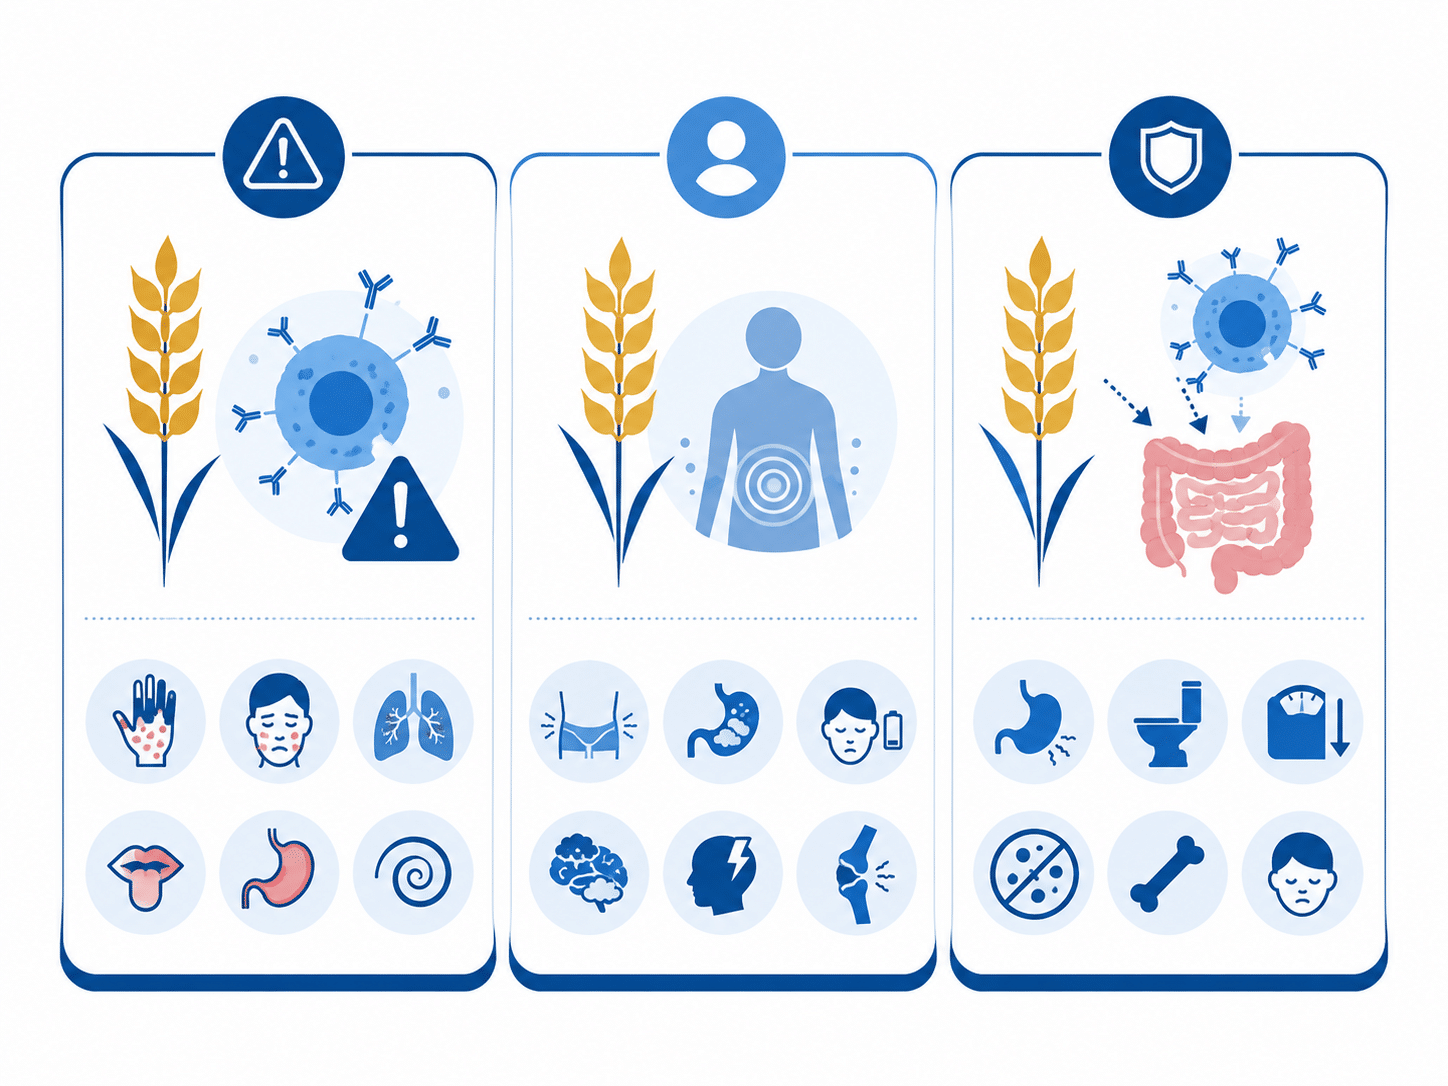 One note on gluten sensitivity: the trigger may be gluten itself, fermentable carbohydrates called FODMAPs, or other components of wheat. That uncertainty is part of why it is so hard to test for.
The best order to test in
- Keep eating gluten.
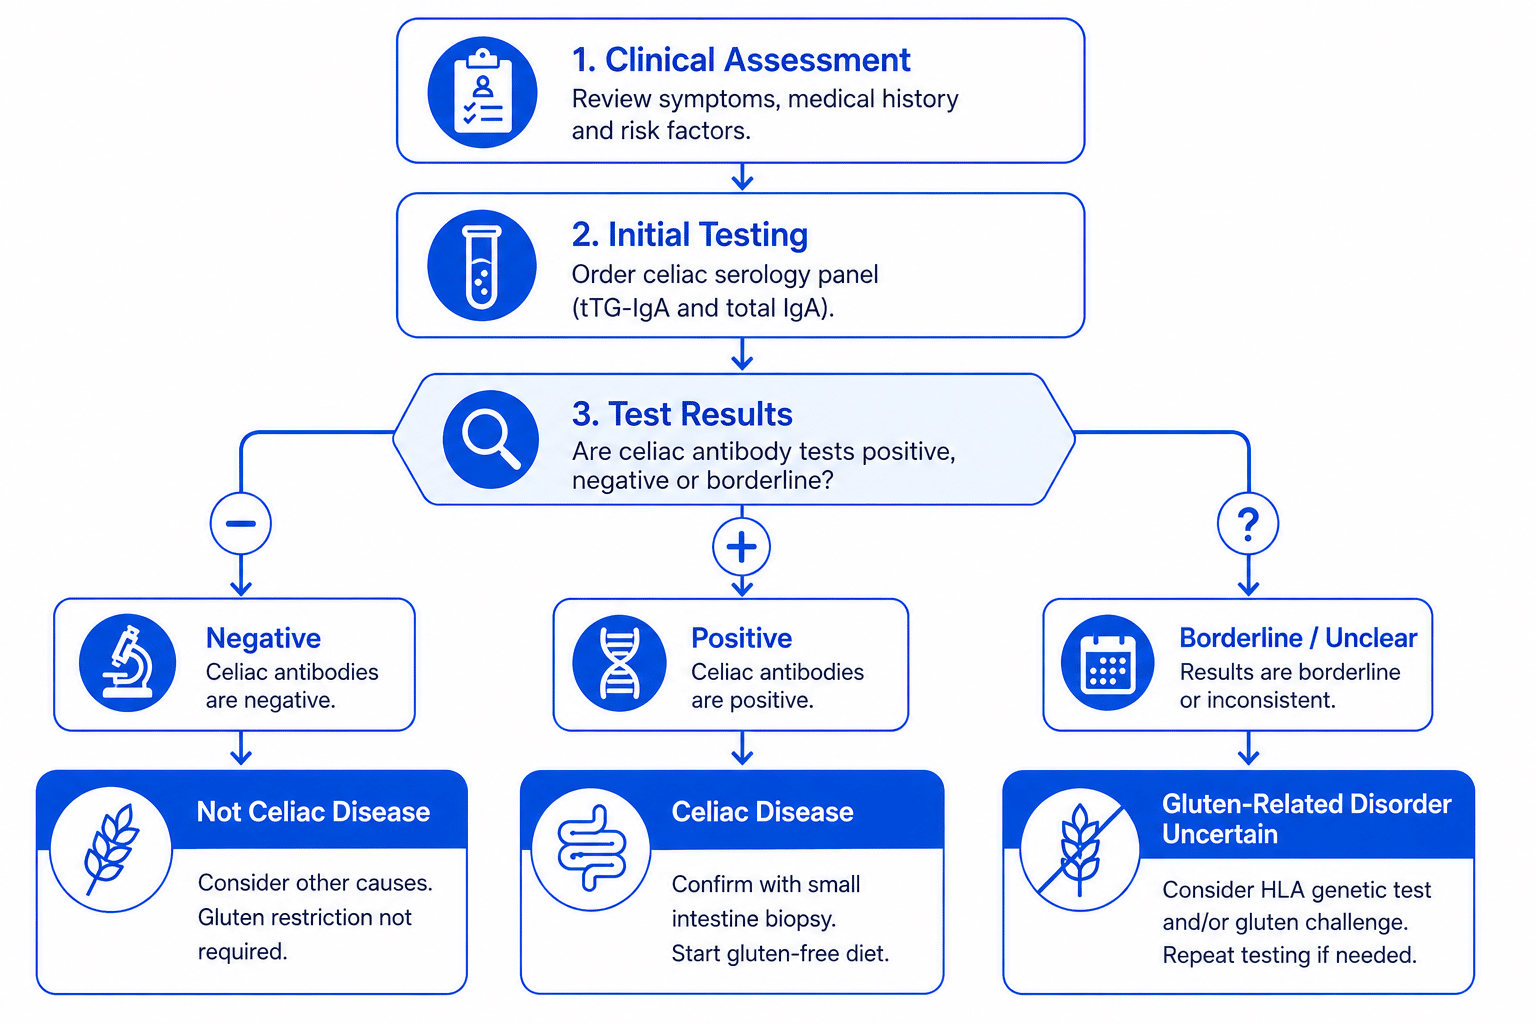
- Celiac blood test first — tTG-IgA plus total IgA.
- Allergist testing if your reactions are fast or allergic.
- Elimination trial only after both are ruled out.
What are the three conditions gluten can trigger?
Wheat allergy
A wheat allergy is a classic allergic reaction. Your immune system makes IgE antibodies (the same antibodies behind peanut and shellfish allergies) against proteins in wheat, and reactions come on fast — usually within minutes to two hours. Symptoms can include hives, swelling, a stuffy or runny nose, wheezing, vomiting, and in serious cases anaphylaxis, a whole-body reaction that needs emergency treatment.
Wheat allergy is a reaction to wheat proteins, not to gluten as a category, so many people with a wheat allergy can eat rye and barley without trouble. That should still be individualized rather than assumed, especially if your past reactions were severe or if testing points to other grain allergies — some people react to more than one grain, or have cross-reactivity between them. Let your allergist guide what you reintroduce and when.
Studies that confirmed diagnoses with a supervised food challenge put the prevalence at roughly 0.2% to 1%. It is more common in children, and most grow out of it — about 65% by age 12, and the large majority by 16. There is also an unusual form where a reaction only happens when wheat is followed by exercise.
Non-celiac gluten sensitivity
Gluten sensitivity describes people who feel clearly worse after eating gluten but do not have a wheat allergy or celiac disease. It does not damage the intestine and it does not involve the same autoimmune process. Symptoms tend to be bloating, abdominal pain, changes in bowel habits, tiredness, headache, and difficulty concentrating.
It is the least understood of the three. Nobody knows how common it is, partly because there is no test that identifies it. Some research also suggests that for a subset of people, other components of wheat — including fermentable carbohydrates known as FODMAPs — may be doing more of the work than gluten itself.
Celiac disease
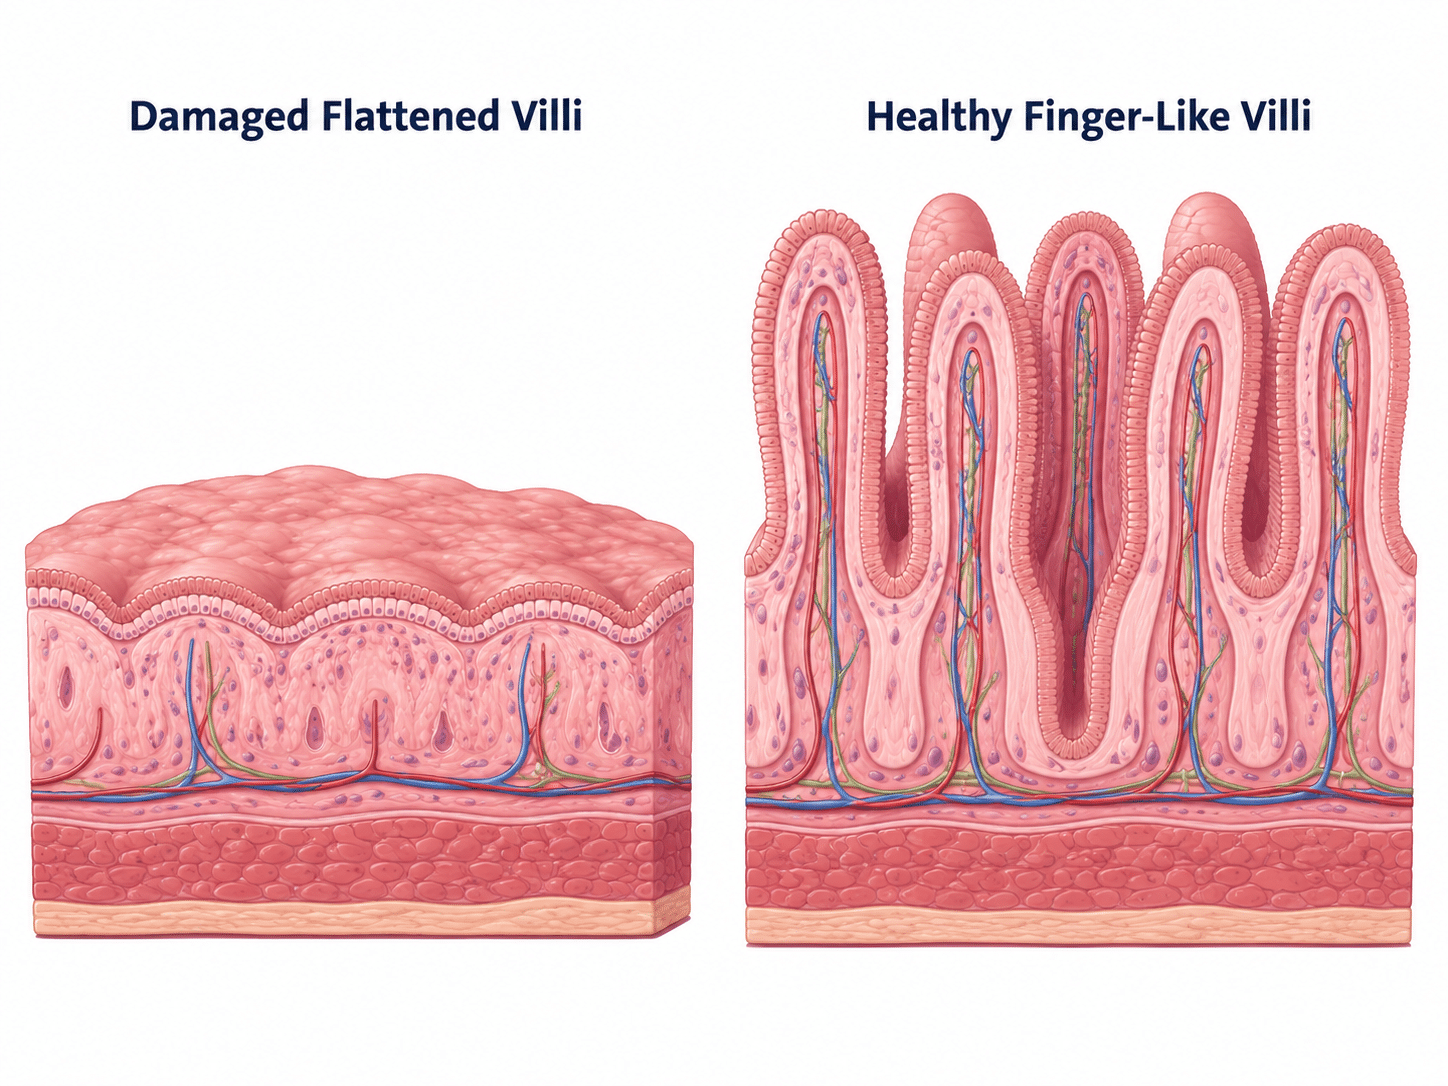
Celiac disease is an autoimmune condition. When you eat gluten, your immune system attacks the lining of your own small intestine, flattening the finger-like villi that absorb nutrients. About 1% of Americans have it. Because it can be silent for years, plenty of people are causing damage without any digestive complaints at all, and untreated celiac disease is linked to anemia, thinning bones, and rarely, intestinal lymphoma.
This article covers celiac disease only far enough to help you tell it apart from the other two. For the full picture — how it is confirmed, what it does over time, and how to manage the gluten-free diet — see celiac disease and type 1 diabetes.
How do the symptoms differ?
There is real overlap here, which is exactly why self-diagnosis goes wrong so often. What separates the three is less the symptom list than the timing and the extra features that show up alongside the digestive complaints.
| Feature | Wheat allergy | Gluten sensitivity | Celiac disease |
|---|---|---|---|
| Hives or swelling | Common | No | No |
| Trouble breathing | Possible | No | No |
| Bloating, diarrhea | Possible | Common | Common |
| Fatigue, brain fog | Uncommon | Common | Common |
| Anemia, bone loss | No | No | Possible |
| No symptoms at all | No | No | Possible |
The short version: fast reactions with skin or breathing symptoms point toward allergy. Slower reactions confined to digestion and energy could be either of the other two, and only testing separates them.
How is each condition diagnosed?
Wheat allergy
This one belongs with an allergist. They will take your history and typically use a skin prick test, a blood test for wheat-specific IgE, or both. Neither is conclusive on its own, so a supervised oral food challenge remains the most reliable way to confirm it.
Do not test this one yourself. Eating wheat at home to see what happens is not a safe way to check for an allergy. IgE reactions can escalate quickly, and food challenges are done in a medical setting precisely because emergency treatment needs to be on hand.
If you have ever had anaphylaxis, wheezing, throat tightness, or rapid swelling after eating, ask your allergist whether you need an epinephrine auto-injector and a written emergency action plan. Both are standard for people at risk of severe reactions.
Celiac disease
Testing starts with blood work: tissue transglutaminase IgA (tTG-IgA) measured alongside total IgA. The total IgA matters because roughly 2% to 3% of people with celiac disease are IgA deficient, which can make the tTG result read falsely negative. If the blood test is positive, an upper endoscopy with biopsies confirms the diagnosis by showing the damage directly.
tTG-IgA is the best single blood test available, but it is not flawless. Real-world sensitivity spans roughly 63% to 93%, so if your doctor strongly suspects celiac disease and the blood test comes back negative, endoscopy is still worth discussing.
One exception is worth knowing if you are a parent. In some children with very high celiac antibody levels, specialists can confirm the diagnosis without a biopsy using strict criteria — typically tTG-IgA at more than ten times the upper limit of normal, plus a positive endomysial antibody test on a second blood sample. This is a specialist decision, not a shortcut to ask for, and many children still need endoscopy to confirm.
Gluten sensitivity
There is no blood test for gluten sensitivity. It is a diagnosis of exclusion: wheat allergy and celiac disease are ruled out first, and then you and your doctor work through a structured removal and reintroduction of gluten to see whether symptoms track with it reliably. Research settings use a placebo-controlled challenge, which is rarely practical in ordinary care.
Why do you have to keep eating gluten until you are tested?
This is the single most common mistake, and it costs people months. Both the celiac blood test and the biopsy measure your immune system’s response to gluten. Take gluten away and the antibodies fall, the intestine starts to heal, and the tests come back negative whether or not you have the disease. You end up with no answer and no idea how strict you need to be.
So stay on gluten until testing is finished. If you have already gone gluten-free and feel better, do not just start eating it again on your own — ask your doctor about a supervised gluten challenge. Genetic testing for HLA-DQ2 and HLA-DQ8 is another option, since it stays valid no matter what you are eating. A negative result essentially rules celiac disease out. A positive result only shows you carry the risk genes, which roughly a third of the general population does, so it cannot confirm anything on its own.
What does this mean if you have diabetes?
Celiac disease and type 1 diabetes are both autoimmune conditions, and they share the same genetic risk markers — HLA-DQ2 and HLA-DQ8. That is why they travel together so often. Pooled research puts biopsy-confirmed celiac disease at around 6% of people with type 1 diabetes, roughly one in sixteen, compared with about 1% in the general population. Rates run higher in children than adults.
Most people with both conditions have no obvious digestive symptoms. Instead, celiac disease tends to announce itself through your diabetes: unexplained low blood sugars below 70 mg/dL (3.9 mmol/L), readings that swing without a clear reason, or slowed growth in children. A damaged intestine absorbs carbohydrate unpredictably, so food that used to behave one way suddenly does not, and insulin timing stops lining up.
Because of that, the ADA Standards of Care in Diabetes 2026 (Section 14) recommends screening youth with type 1 diabetes for celiac disease using tTG-IgA with total IgA soon after the diabetes diagnosis, repeating at 2 years and again at 5 years, and screening more often for anyone with symptoms or a first-degree relative with celiac disease.
For adults with type 1 diabetes, screening is more individualized and there is no fixed schedule. Testing is worth raising with your doctor if you have unexplained low blood sugars, iron-deficiency anemia, unintended weight loss, ongoing diarrhea, thinning bones, or a first-degree relative with celiac disease.
Wheat allergy and gluten sensitivity have no known special relationship with diabetes of either type. If you have type 1 diabetes and gluten is bothering you, celiac disease is the possibility worth ruling out first.
How do the treatments differ?
| Condition | What treatment looks like |
|---|---|
| Wheat allergy | Avoid wheat. Rye and barley are usually safe. Your allergist may prescribe an epinephrine auto-injector, and children are often retested over time to see whether they have outgrown it. |
| Gluten sensitivity | Avoid or limit gluten. Many people tolerate small amounts, and the threshold varies from person to person. It may not be permanent, so it is reasonable to reassess later. |
| Celiac disease | Strict, lifelong gluten-free eating. There is no safe amount. Cross-contamination counts too — shared toasters, cutting boards, fryers, bulk bins, and restaurant prep surfaces are all common sources. A dietitian is genuinely worth the appointment. |
If you have diabetes and end up gluten-free, expect to recheck your numbers. Gluten-free breads, flours, and packaged foods often carry different carbohydrate and fiber content than the versions they replace, which changes how they hit your blood sugar. It is a good moment to revisit carb counting rather than assume your usual ratios still apply.
What should you do next?
- Keep eating gluten. Do not cut it out before you are tested.
- Write down your symptoms and how long after eating they appear. Timing is one of the most useful things you can bring to an appointment.
- Ask your doctor for celiac blood work — tTG-IgA together with total IgA.
- If your reactions are fast, or involve hives, swelling, or breathing trouble, ask for a referral to an allergist as well. This does not need to wait for your celiac results.
- If both come back negative and gluten still seems to be the culprit, talk with your doctor about a structured elimination and reintroduction trial. Irritable bowel syndrome and lactose intolerance produce similar symptoms and are worth ruling out too.
Helpful Resources & Research
- ADA Standards of Care in Diabetes 2026, Section 14: Children and Adolescents — celiac screening recommendations
- American College of Gastroenterology 2023 guideline — diagnosis and management of celiac disease
- Celiac Disease Foundation — symptoms and diagnosis
- Salerno Experts’ Criteria — diagnosis of non-celiac gluten sensitivity
- Systematic review and meta-analysis — associations between celiac disease and type 1 diabetes
- Celiac Disease and Type 1 Diabetes — the full picture on celiac disease
Frequently Asked Questions
What is the difference between gluten sensitivity and celiac disease?
Celiac disease is autoimmune — gluten causes your immune system to damage your small intestine, and that damage happens whether or not you feel it. Gluten sensitivity causes symptoms without any intestinal damage or autoimmune reaction. Celiac disease requires strict lifelong gluten avoidance, while many people with gluten sensitivity tolerate small amounts.
Can I still be tested for celiac disease if I already stopped eating gluten?
Not accurately. Celiac blood tests and biopsies measure your response to gluten, so removing it makes the results unreliable and often falsely negative. Talk to your doctor about a supervised gluten challenge, or about HLA-DQ2 and HLA-DQ8 genetic testing, which stays valid regardless of what you are eating.
Is a wheat allergy the same thing as gluten intolerance?
No. A wheat allergy is an IgE allergic reaction to wheat proteins, and it can involve hives, swelling, or trouble breathing within minutes. Gluten intolerance, or non-celiac gluten sensitivity, causes slower digestive and energy symptoms and responds to gluten in wheat, rye, and barley rather than to wheat alone.
How common is celiac disease in people with type 1 diabetes?
About 6% of people with type 1 diabetes have biopsy-confirmed celiac disease, roughly one in sixteen, compared with about 1% of the general population. Rates are higher in children than in adults. Both conditions share the HLA-DQ2 and HLA-DQ8 genetic markers, which is why they occur together so often.
Can you have celiac disease without any symptoms?
Yes, and it is common. Many people, especially those with type 1 diabetes, have no digestive complaints at all while intestinal damage continues. This is why the ADA recommends routine screening for children with type 1 diabetes rather than waiting for symptoms to appear.
Is there a blood test for gluten sensitivity?
No. There is no validated blood test or biomarker for non-celiac gluten sensitivity. It is diagnosed by first ruling out wheat allergy and celiac disease, then removing and reintroducing gluten in a structured way to see whether symptoms track with it. Anti-gliadin (AGA) antibody testing is not reliable for this.
Can celiac disease cause unexplained low blood sugars?
It can. Damaged intestinal villi absorb carbohydrate less predictably, so food may hit your bloodstream more slowly or less completely than your insulin dose assumes. Unexplained readings below 70 mg/dL (3.9 mmol/L), erratic glucose patterns, or slowed growth in children are all reasons to ask about celiac screening.
Do children outgrow a wheat allergy?
Most do. Research suggests roughly 65% of children have outgrown a wheat allergy by age 12, and the large majority by 16. Your allergist can retest periodically and may use a supervised oral food challenge to confirm whether wheat can be safely reintroduced.
If I have a wheat allergy, do I need to avoid rye and barley too?
Often not, but do not assume it. Wheat allergy is a reaction to proteins in wheat specifically, so rye and barley are frequently tolerated. Some people do have multiple grain allergies or cross-reactivity, though, so let your allergist decide what you reintroduce — particularly if your past reactions were severe. This is a key difference from celiac disease and gluten sensitivity, which respond to gluten in all three grains.
How much gluten do I need to eat before a celiac test?
Your doctor should set the amount and the duration, because protocols vary. As a general guide, gluten challenge plans commonly use 3 to 10 grams of gluten a day — roughly one to four slices of bread, depending on the loaf — for 6 to 12 weeks. If you are currently eating gluten normally, the important thing is simply not to cut back in the run-up to your test.
Last Updated on August 27, 2026