
Hypoglycemia symptoms are your body’s warning that your blood sugar has dropped too low—usually below 70 mg/dL (3.9 mmol/L) if you have diabetes. Shaky hands, sweating, a pounding heart, sudden hunger, or trouble thinking clearly can all be signs of a low. Some people notice symptoms at 60–70 mg/dL (3.3–3.9 mmol/L). Others don’t notice anything until it’s much lower, and some feel “low” even when their blood sugar is in a normal range.
Spotting these signs early lets you treat a mild low before it becomes serious. This page explains what low blood sugar feels like, why symptoms vary, what to watch for at night, and when a low becomes an emergency. Whether you live with type 1 diabetes or use insulin for type 2 diabetes, recognizing your warning signs is a key safety skill.
→ Jump to Frequently Asked Questions
Series navigation: Hypoglycemia Overview | Symptoms | Prevention | Treatment | Hypoglycemia Unawareness | Staying Calm When Assisting Someone
At a Glance: How Low Is Too Low?
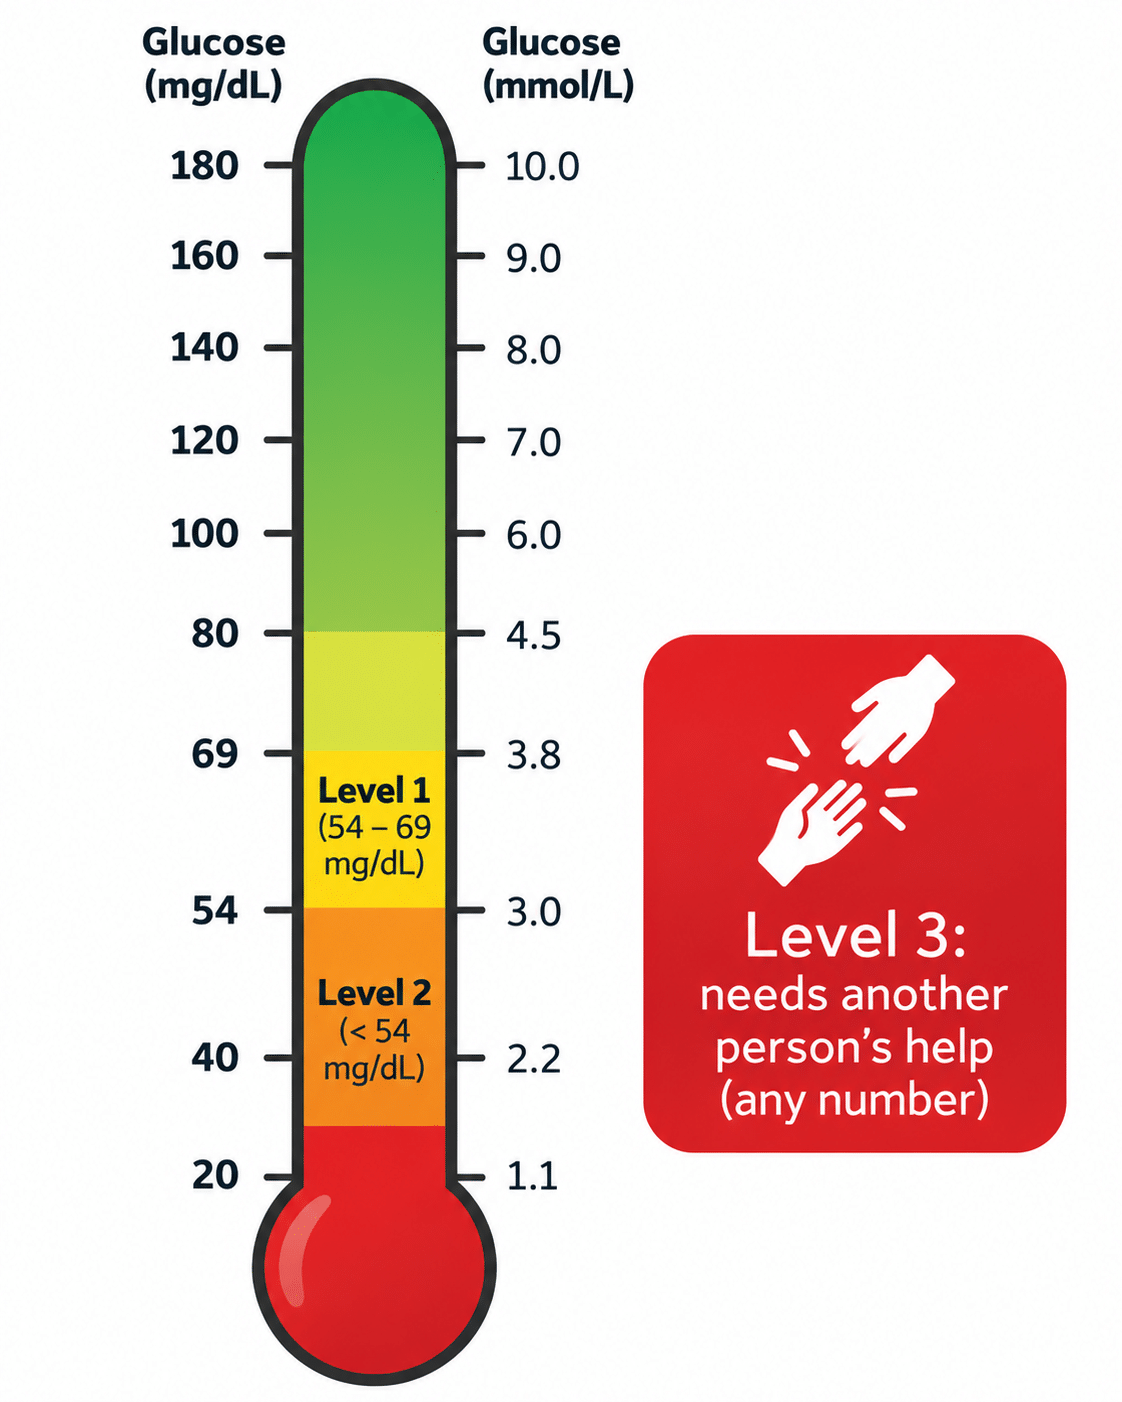
The American Diabetes Association groups low blood sugar into three levels (ADA 2026):
| Level | Blood sugar | What it means |
|---|---|---|
| Level 1 | 54–69 mg/dL (3.0–3.8 mmol/L) | Low; treat right away |
| Level 2 | Below 54 mg/dL (3.0 mmol/L) | Serious low; treat immediately |
| Level 3 | No specific glucose number | Severe low that needs another person’s help |
Level 3 is defined by what happens—needing someone else’s help to recover—not by a glucose number. Any Level 2 or Level 3 low is a reason to review your treatment plan with your care team, even if you recover quickly.
Think you’re low? Check your blood sugar now. If it’s below 70 mg/dL (3.9 mmol/L), treat it with fast-acting carbs and recheck in 15 minutes. If you can’t check, treat anyway. See the steps below or our full treatment guide.
What does low blood sugar feel like?
Low blood sugar feels different for everyone, and symptoms can vary from one episode to the next. You might notice a single clear sign, such as trembling hands, or several at once. Many people describe feeling shaky, sweaty, and “off,” with an urgent need to eat.
For context: if your CGM reads 65 mg/dL (3.6 mmol/L) with a downward arrow, you may already feel shaky and hungry—or you may feel nothing at all. That’s why checking your number matters more than waiting to “feel” low.
Feeling low at a normal level. If your blood sugar has been high for a long time, you may feel shaky or “off” as it falls toward the normal range—sometimes even at 100–120 mg/dL (5.6–6.7 mmol/L). This is called relative hypoglycemia. The symptoms are real, but your glucose isn’t actually low, so checking tells you whether to treat. The feeling usually fades as your body adjusts.
Why do lows cause two different types of symptoms?
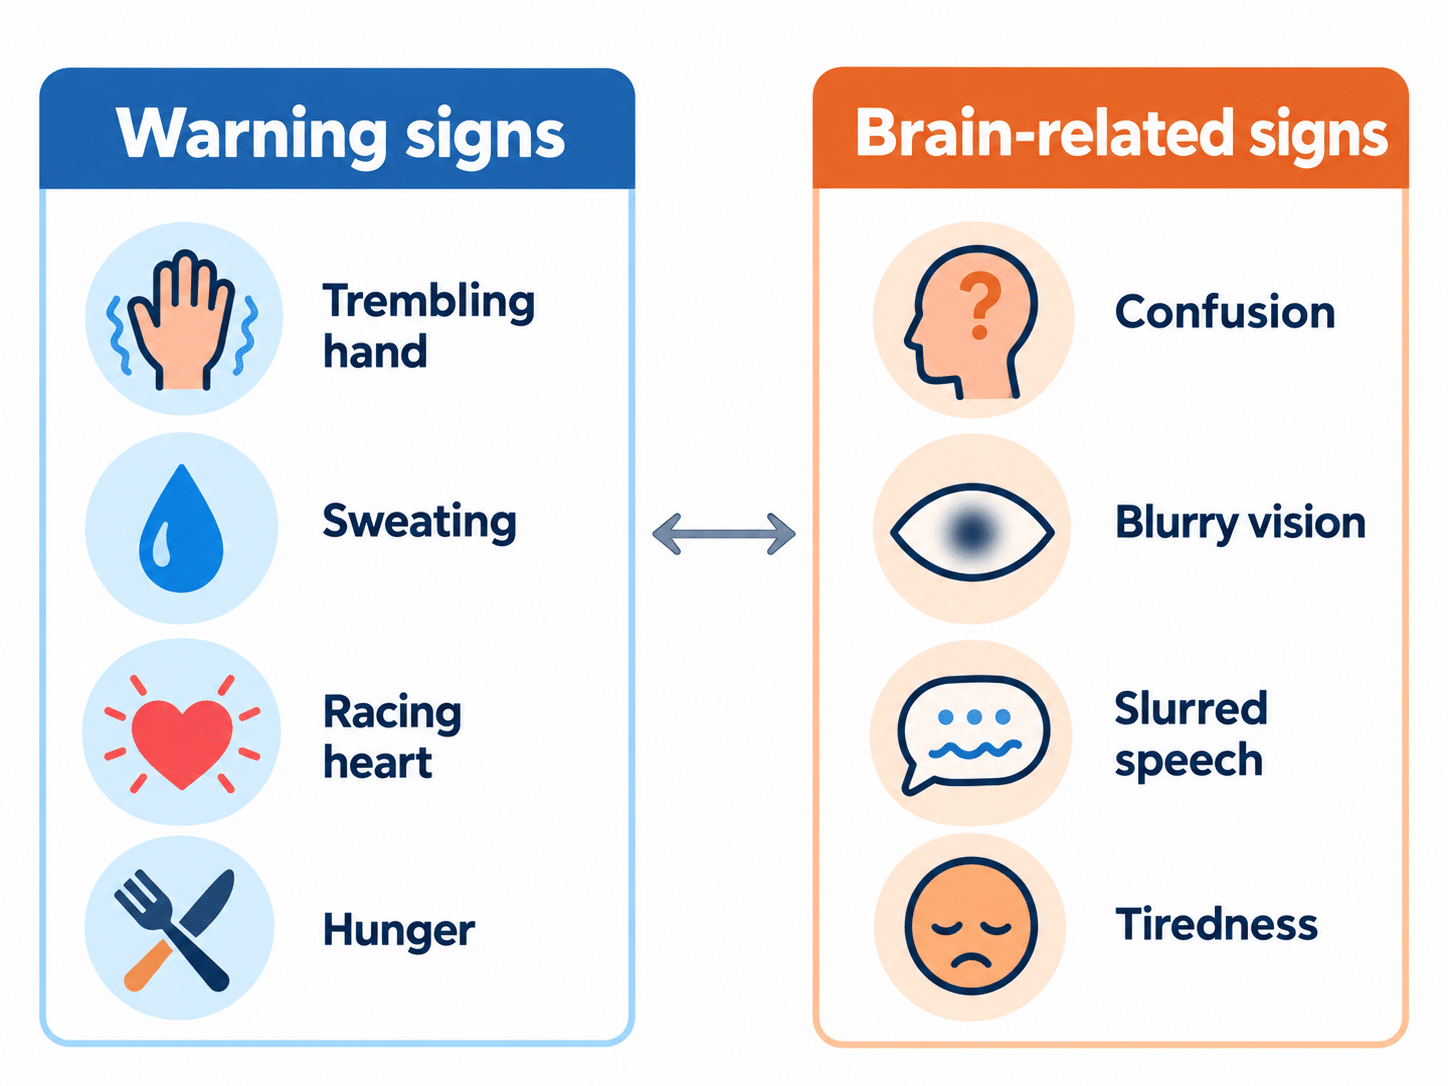
Hypoglycemia symptoms result from two separate effects in your body:
- Warning symptoms (stress hormones). When your blood sugar drops, your body releases stress hormones such as adrenaline (epinephrine) to raise it. These hormones cause the classic warning signs: shakiness, sweating, a racing heart, and hunger. Doctors call these “autonomic” symptoms.
- Brain-related symptoms (neuroglycopenia). Your brain runs almost entirely on glucose. When it doesn’t get enough, you may experience confusion, poor concentration, slow reactions, or unusual behavior. Neuro means brain or nerves, glyco means sugar, and penia means shortage.
Warning symptoms often appear before changes in thinking or coordination, though the order varies. People who have lost some of their warning signs—called hypoglycemia unawareness—may become confused without first feeling shaky, sweaty, or hungry. Headache and nausea can occur with either type of low.
When your brain is low on fuel, you may not realize how impaired you are, so others sometimes notice a low before you do. If you’re the one helping, see our guide to staying calm while assisting someone with a low.
What are the early warning signs of low blood sugar?
These stress-hormone symptoms often appear first. If you notice any of them and you’re at risk for lows, check your blood sugar with your meter or CGM, and treat if you’re low.
- Shaking or trembling
- Sweating, chills, or clammy skin
- Fast or pounding heartbeat (palpitations)
- Sudden hunger
- Anxiety, nervousness, or a feeling of doom
- Tingling or numbness, often around the lips, tongue, or cheeks
- Pale skin (color draining from the face)
- Headache or nausea
Brain-related symptoms often mean your low is getting deeper—though for some people they are the first sign. Take them seriously, even if they seem mild:
- Dizziness or feeling lightheaded
- Blurred or double vision
- Confusion, “brain fog,” trouble concentrating, or trouble finding words
- Slurred speech
- Clumsiness, poor coordination, or slow reaction time
- Irritability, sudden mood swings, or unusual behavior
- Sudden tiredness, sleepiness, or weakness
Don’t drive, operate machinery, or try to “push through” a brain-related low. Treat it first, and wait until your blood sugar is back in range and you feel clear-headed.
What are the signs of low blood sugar at night?
Lows during sleep are common if you use insulin, and they’re easy to miss because you may sleep right through the warning signs. A nighttime low is more likely after an active day, exercise close to bedtime, drinking alcohol in the evening, or taking more insulin than you need.
Signs during the night
- Nightmares or vivid, disturbing dreams
- Waking up sweaty, with damp pajamas or sheets
- Restless sleep or waking up often
- Crying out, talking, or unusual movements during sleep (a bed partner may notice these first)
- A racing heart when you wake up
Next-morning clues
- A headache when you wake up
- Feeling unusually tired, groggy, irritable, or confused after a full night’s sleep
- Damp sheets or pillowcase
What about a high morning reading? It does not necessarily mean your blood sugar dropped overnight. The dawn phenomenon (early-morning hormones that raise blood sugar), too little overnight insulin, and late snacks are more common causes than a “rebound” from a night low. Review your overnight CGM data before changing any insulin dose. Learn more about high blood sugar.
Use technology but know its limits. A continuous glucose monitor (CGM) with a low alert is the best everyday tool for detecting overnight lows, and an automated insulin delivery (AID) system can reduce or pause insulin as your blood sugar falls. However, a CGM can miss a low, lag behind a rapid drop, or show a false low.
Compression lows can cause false nighttime alarms. When you lie on your sensor, the pressure squeezes the skin and tissue around it and briefly slows blood flow to that spot. The sensor then reads falsely low—often a sharp drop that bounces back once you roll off it—even though your blood sugar is fine. If you have no symptoms, confirm with a fingerstick; if you feel low or can’t check, treat it.
Why do hypoglycemia symptoms vary so much from person to person?
Your symptoms can vary due to:
- How quickly your blood sugar drops. A rapid drop can feel intense, sometimes before you reach 70 mg/dL (3.9 mmol/L).
- Recent lows. Repeated lows can dull your warning signs for a time.
- How long you’ve had diabetes. Warning signs often weaken over many years.
- Age. Older adults may show fewer warning signs, and brain-related symptoms can be mistaken for confusion or dementia.
- Medications. Beta blockers (common heart and blood pressure medications) can mask shakiness and a racing heart.
- Alcohol. Alcohol can blunt your awareness of low blood sugar and also lower your blood sugar for hours after drinking.
- Sleep. Nighttime lows are harder to notice.
If you no longer feel lows the way you used to, read our page on hypoglycemia unawareness. The ADA notes that carefully avoiding lows for several weeks often helps warning signs return.
Which diabetes medications can cause low blood sugar?
Lows can happen with any type of insulin. Among diabetes pills, the main ones that cause lows are medicines that make your pancreas release more insulin. These are called insulin secretagogues.
| Medicine type | Examples | Risk of lows |
|---|---|---|
| Insulin | All types | Significant risk; varies by type, dose, and routine |
| Sulfonylureas | Glipizide, glyburide, glimepiride | Significant risk; lows can last longer or come back |
| Meglitinides | Repaglinide (Prandin), nateglinide (Starlix) | Can cause lows, especially if a meal is skipped |
| Other pills and shots | Metformin, GLP-1s, SGLT2s, DPP-4s, pioglitazone | Low risk unless combined with insulin or a sulfonylurea |
Sulfonylurea lows—especially those from glyburide—can last for hours and recur after treatment, particularly in older adults or people with kidney disease. If a sulfonylurea-related low is severe or keeps coming back, seek urgent medical care. Report any lows on these medicines to your clinician promptly.
GLP-1 agonists, SGLT2 inhibitors, metformin, DPP-4 inhibitors, and pioglitazone rarely cause lows on their own. However, when one of them is added to insulin or a sulfonylurea, lows become more likely. Your clinician may lower your insulin or sulfonylurea dose when starting one of these medicines.
Can a CGM warn you before you feel a low coming?
Yes. A continuous glucose monitor checks your sugar every few minutes and can sound an alarm when you’re low—or heading there. This matters most when your warning signs are weak or you’re asleep. The ADA now recommends CGM from the time of diagnosis for adults who use insulin or take other diabetes medications that can cause lows (ADA 2026, Recommendation 9.25).
A few tips for using your CGM to detect lows:
- Set your low alert to a level that gives you time to act. Many people use 70 mg/dL (3.9 mmol/L) or slightly higher.
- Turn on predictive “urgent low soon” alerts if your device supports them.
- If your symptoms don’t match your reading, confirm with a fingerstick; sensors lag when glucose changes rapidly.
If you use a CGM, the ADA goal for most adults is less than 4% of the day (about 1 hour) below 70 mg/dL (3.9 mmol/L) and less than 1% below 54 mg/dL (3.0 mmol/L). Older or higher-risk adults aim for less than 1% below 70 mg/dL (ADA 2026). Your A1c alone won’t show these lows.
How can family and friends recognize when you are low?

Because brain-related symptoms can be subtle, the people around you are an important safety net. Tell them your usual symptoms. Signs others often notice include:
- Sudden paleness or sweating
- Irritability, arguing, or acting out of character
- A blank or glassy stare
- Confusion or slow answers to simple questions
- Clumsiness or slurred speech that can look like being drunk
In young children, low blood sugar may appear as crankiness, tantrums, sudden quietness, or unusual sleepiness. Parents and caregivers should check blood sugar whenever a child’s behavior changes suddenly.
Show family, close friends, and coworkers where you keep fast-acting sugar and glucagon, and teach them how to use them. Wearing a medical ID helps strangers and first responders recognize that unusual behavior may be due to low blood sugar, not intoxication.
When is low blood sugar an emergency?
A low becomes Level 3, or severe, when the person needs help from someone else to recover, regardless of the glucose level. That doesn’t always mean passing out—someone who is awake but too confused to treat themselves is also experiencing a severe low.
If they’re awake and can swallow safely, help them take fast-acting sugar, such as glucose tablets, glucose gel, or juice, and stay with them. If they don’t improve within 15 minutes or get worse, give glucagon if available and call 911.
Give glucagon immediately if available, and call 911 if the person:
- Is unconscious or won’t respond
- Has a seizure
- Can’t swallow safely
Never give food, liquids, or glucose gel by mouth to someone who can’t swallow safely. If an unconscious person is breathing, roll them onto their side (glucagon can cause vomiting), stay with them, and follow the dispatcher’s instructions. If glucagon isn’t available, call 911 right away.
The ADA recommends glucagon for everyone who takes insulin or is at high risk of low blood sugar and prefers ready-to-use forms that don’t require mixing (ADA 2026). Examples include nasal glucagon (Baqsimi) and prefilled glucagon pens and syringes (Gvoke). For step-by-step instructions, see our low blood sugar treatment page.
What should you do if you notice symptoms?
Here is the short version. Our treatment page details each step.
- Check your blood sugar with your meter or CGM. If you can’t check, treat anyway—it’s safer.
- Treat a reading below 70 mg/dL (3.9 mmol/L) with fast-acting carbs. For most people, that’s 15 grams, such as 4 glucose tablets or ½ cup (4 oz) of juice or regular soda. With an AID system, 5–10 grams is often enough because the system has already reduced insulin (ADA 2026); a deeper low, exercise, or a lot of active insulin may require more. Follow your care team’s plan.
- Recheck in 15 minutes. If you’re still below 70 mg/dL (3.9 mmol/L), treat again. CGM readings lag during recovery: if your CGM still reads low but the arrow is trending up or you feel better, confirm with a fingerstick before eating more to avoid overtreating.
- Eat a snack once you’re back in range if your next meal is more than an hour off.
If you take acarbose or miglitol, always use glucose tablets or gel—table sugar or other carbs won’t raise your blood sugar quickly enough. For quick carb options, see how to raise low blood sugar quickly and safely. To prevent lows in the first place, visit our prevention page.
Series navigation: Hypoglycemia Overview | Symptoms | Prevention | Treatment | Hypoglycemia Unawareness | Staying Calm When Assisting Someone
Helpful Resources & Research
- American Diabetes Association: Low Blood Glucose (Hypoglycemia)
- American Diabetes Association: Signs, Symptoms, and Treatment for Hypoglycemia
- ADA Standards of Care 2026, Section 6: Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises (Diabetes Care)
- ADA Standards of Care 2026, Section 9: Pharmacologic Approaches to Glycemic Treatment (Diabetes Care)
- NIDDK: Low Blood Glucose (Hypoglycemia)
- CDC: Low Blood Sugar (Hypoglycemia)
- Mayo Clinic: Hypoglycemia — Symptoms and Causes
Frequently Asked Questions About Hypoglycemia Symptoms
What blood sugar level is considered low?
For most people with diabetes, low blood sugar is below 70 mg/dL (3.9 mmol/L). The ADA defines 54–69 mg/dL (3.0–3.8 mmol/L) as Level 1 and recommends treating it right away. Below 54 mg/dL (3.0 mmol/L) is Level 2, a serious low. Level 3 is any low that requires someone else’s help, regardless of the number.
What are the early signs of low blood sugar?
Early signs often include shakiness, sweating, a fast heartbeat, sudden hunger, and feeling anxious or nervous. These symptoms stem from stress hormones your body releases to raise your blood sugar. Some people—especially those with hypoglycemia unawareness—notice confusion or difficulty concentrating first.
Can I have low blood sugar symptoms with a normal reading?
Yes. If your blood sugar has been high for a long time, you may feel low as it falls toward normal, sometimes even at 100–120 mg/dL (5.6–6.7 mmol/L). This is called relative hypoglycemia; your glucose isn’t actually low, so check before treating. Tell your care team if it’s frequent or bothersome.
Is it low blood sugar or anxiety?
Shakiness, sweating, a racing heart, and a sense of dread can occur with both. The only way to tell is to check your blood sugar. If you’re below 70 mg/dL (3.9 mmol/L), treat it as a low. If your number is in range but these feelings persist, talk with your clinician—anxiety and panic attacks are common and treatable.
Why does my CGM alarm low at night even though I feel fine?
Often it’s a “compression low.” Pressure from lying on your sensor slows blood flow to the tissue around it, so the reading dips sharply, then bounces back when you roll over. Your actual blood sugar may be normal. If you have no symptoms, confirm with a fingerstick. If you feel low or can’t check, treat it.
Can low blood sugar occur without any symptoms?
Yes. This is called hypoglycemia unawareness, and it’s more common after repeated lows or after many years with diabetes. Beta blockers and alcohol can also mask symptoms. Carefully avoiding lows for several weeks often helps warning signs return.
Do GLP-1 medications like Ozempic cause low blood sugar?
On their own, GLP-1 medicines rarely cause low blood sugar. The risk increases when they are taken with insulin or a sulfonylurea such as glipizide. Your clinician may lower those doses when you start a GLP-1.
Can you have low blood sugar even if you don’t have diabetes?
It’s uncommon, but yes. Causes include heavy drinking without eating, certain medications, serious liver or kidney disease, some hormone disorders, and stomach surgery. Doctors confirm it using Whipple’s triad: symptoms, a low glucose level measured at the time, and relief once glucose is raised. If this happens to you, see your doctor.
How long do low blood sugar symptoms last after treatment?
Shakiness and sweating usually ease within 15 to 30 minutes once your blood sugar is above 70 mg/dL (3.9 mmol/L). A headache, tiredness, or trouble focusing can linger for a few hours, especially after a deeper low. If lows keep coming back—especially when taking a sulfonylurea—seek medical care.
When should I call 911 for low blood sugar?
Call 911 if someone is unconscious, has a seizure, or can’t swallow safely—and give glucagon immediately if it’s available. Also call if someone who is confused doesn’t improve within 15 minutes after taking sugar. Never put food or drink in the mouth of someone who can’t swallow safely.
Medical disclaimer: This content is for education and does not replace individualized medical advice. Seek urgent help for severe lows (seizure, unconsciousness, or inability to swallow safely), and talk with your clinician if you’re having frequent or unexplained low blood sugars.
Last Updated on October 19, 2026